

For most people over 40 with a meniscus tear that doesn't lock the knee, a structured physio and exercise programme works about as well as keyhole surgery, according to two large randomised trials. A torn meniscus is damage to one of the two rubbery cartilage cushions inside the knee. Younger people with a sudden twisting injury, and anyone whose knee is truly locked, may still need a surgical opinion. And here's the twist: many meniscus tears seen on MRI aren't causing any pain at all.
Key takeaways
- Two kinds of tear: a sudden traumatic tear (usually a twisting injury in younger, active people) and a gradual degenerative tear (common from middle age, often without a clear injury).
- For degenerative tears without locking, exercise therapy matched keyhole surgery for knee function at 2 years in trials from Norway and the Netherlands.
- About 1 in 5 over-40s have a meniscus tear on MRI with no knee pain at all, so the tear isn't always the cause.
- A truly locked knee (it won't straighten) needs prompt assessment.
- Most people improve over 8–12 weeks of progressive strengthening.
What is a meniscus tear?
Each knee has two menisci: C-shaped pads of cartilage that sit between the thigh bone and shin bone. They spread load, add stability and help the joint glide.
There are two main types of tear:
| Traumatic tear | Degenerative tear | |
|---|---|---|
| Who | Usually under 40, sporty | Usually over 40 |
| How | Twisting on a bent knee: football, netball, skiing, 5-a-side | Gradual, often no clear injury, sometimes after a deep squat or kneeling |
| Often with | ACL or other ligament injury | Early osteoarthritis changes |
| Typical first step | Assessment; surgical opinion if the knee locks, is unstable or a repairable tear is likely | Exercise-based rehab |
Common symptoms: pain along the inside or outside of the joint line, swelling that builds over a day or so, pain with deep bending, squatting or twisting, and catching or clicking.
The myth: "A tear on the MRI means you need it fixed"
Scans are good at finding tears. They're less good at telling you whether a tear is the reason you hurt. A 2019 review of 63 studies looked at MRI scans of 5,397 knees in adults with no knee pain and no injury:
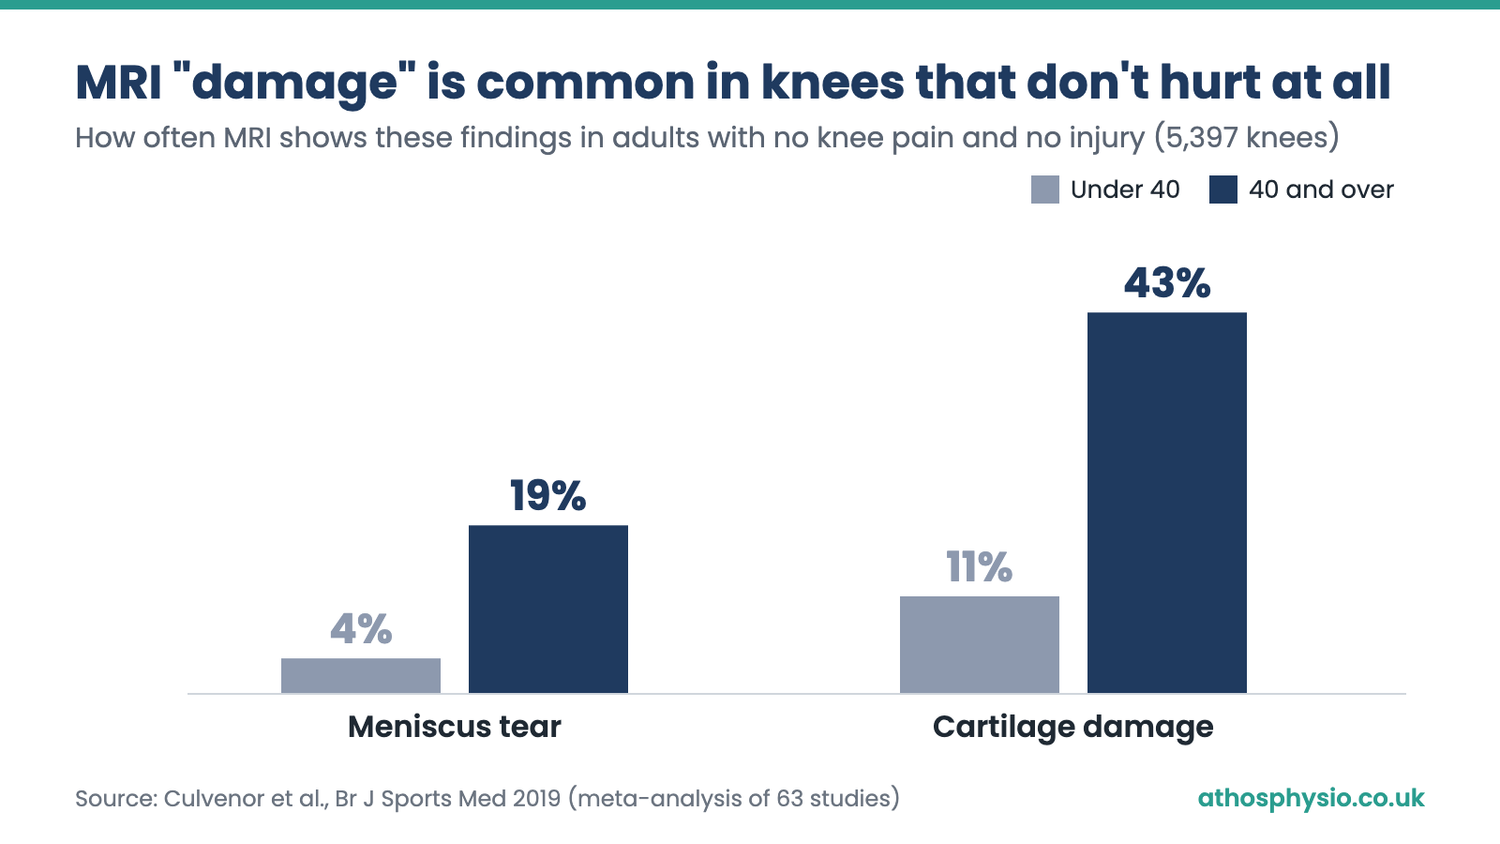
- 4% of under-40s had a meniscus tear
- 19% of over-40s had a meniscus tear
So in middle age, a tear can be a normal finding, much like grey hair. If your knee pain started recently, the tear might have been there for years. That's why decisions should be based on your symptoms and examination, not the scan alone.
Surgery or physio? What the trials show
The Norwegian trial (BMJ, 2016) randomised 140 adults with an average age of 50 and a degenerative tear to either 12 weeks of supervised exercise or keyhole surgery to trim the tear (partial meniscectomy). At 2 years there was no clinically relevant difference in knee function. The exercise group had stronger thighs at 3 months. 19% of the exercise group later chose surgery, with no extra benefit.
The ESCAPE trial (JAMA, 2018) randomised 321 people aged 45–70 with tears that didn't lock the knee. Physio was 16 sessions over 8 weeks. Over 2 years, knee function improved by 26 points after surgery and 20 points after physio, a difference small enough that physio was judged "non-inferior", meaning not meaningfully worse. Repeat surgery and extra visits for knee pain were slightly more common in the surgery group.
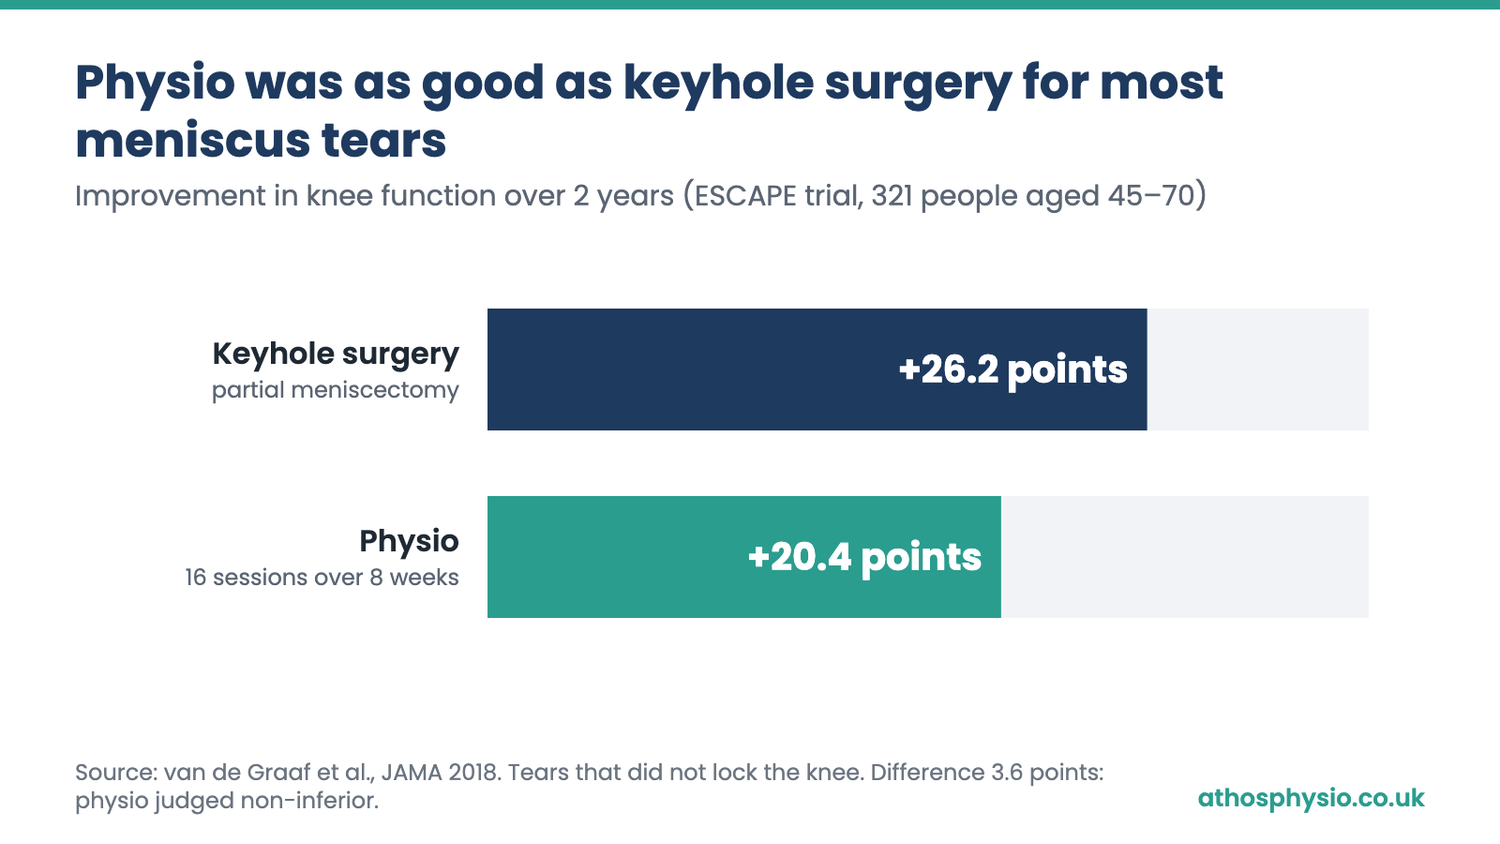
How much weight to put on this: these are large, well-run trials, but they studied middle-aged people with tears that didn't lock the knee. They don't apply to a young footballer with a fresh tear, a locked knee, or a tear alongside an ACL rupture. And choosing physio first doesn't rule out surgery later if you don't improve.
When might you need surgery?

- A locked knee: it suddenly won't straighten fully and stays stuck. A piece of meniscus may be caught in the joint (often called a bucket-handle tear). Get it assessed promptly.
- A traumatic tear in a younger, active person, especially with an ACL injury. Some tears can be repaired rather than trimmed, and a surgeon will advise.
- Symptoms that don't improve after a good 3-month rehab programme.
What helps: a progressive rehab plan
Most meniscus rehab follows the same principles: settle the swelling, restore full movement, then build strength and confidence in bending, twisting and impact. Do the exercises 3 times a week. Discomfort up to 3–4/10 that settles by the next morning is OK. If the knee swells more the next day, drop back.
Stage 1 (weeks 0–2): settle
- Quad sets and straight leg raises: 3 × 10, daily
- Heel slides to restore bending: 2 × 15, daily
- Exercise bike: 10–15 minutes, easy
Stage 2 (weeks 2–6): strengthen
- Sit-to-stand and leg press to a comfortable depth: 3 × 10–12
- Bridges and hamstring curls: 3 × 10–12
- Single-leg balance: 3 × 30 seconds
Stage 3 (weeks 6–12): load and return
- Split squats, step-ups and step-downs: 3 × 8–10, adding weight
- Gradually deeper squats
- If you play sport: jogging, then change of direction and jumping, built up over several weeks
Everyday tips while it settles: avoid deep kneeling and twisting on a bent knee, use the handrail on stairs, and don't push through sharp catching pain.
How long does a meniscus tear take to heal?
Most people with a degenerative tear notice clear improvement within 8–12 weeks of consistent exercise, which matches the length of the programmes in the trials. A traumatic tear in an athlete can take longer, especially after surgical repair, when your surgeon may restrict deep bending for several weeks. Read more in our guide to knee pain when bending.
When to see a physio, GP, 111 or A&E
Go to A&E if you heard a crack, the knee looks misshapen, or you can't put any weight on it after an injury.
See a GP urgently or call 111 if:
- your knee locks and won't straighten
- it swells up within a couple of hours of an injury (this can mean bleeding in the joint, often with a ligament injury)
- it's hot, red and swollen and you feel unwell or feverish
- your calf is swollen, red or warm
See a physio if your knee keeps catching, swelling or giving way, or pain hasn't improved after 2 weeks.
How we help at Athos Physio
Our clinic is inside F45 Training Studio at 77 Piccadilly. We'll assess your knee, explain whether the tear is likely to be the source of your pain, and build a custom rehab and strengthening plan around your goals, whether that's stairs without pain or getting back to 5-a-side. If you need a surgical opinion, we'll tell you why. After surgery, we can guide your post-operative rehab. You don't need a GP referral, and we work with Bupa, WPA, Vitality and Aviva. Book an appointment.
FAQs
Can a torn meniscus heal on its own?
The outer edge of the meniscus has a blood supply and can heal; the inner part has very little. But healing on a scan isn't needed to feel better. Many people with degenerative tears become pain-free with exercise, even though the tear is still visible.
Can I walk on a torn meniscus?
Usually, yes. Walking is generally safe and helps keep the knee moving. Avoid twisting on a bent knee and deep squats while it's sore. If the knee locks or you can't take weight on it, get it checked.
Is meniscus surgery worth it?
For degenerative tears without locking, trials show exercise works about as well as surgery over 2 years, so physio is a sensible first step. Surgery may be the right choice for a locked knee, some traumatic tears in younger people, or symptoms that don't improve with good rehab.
How long is recovery after meniscus surgery?
Recovery after a trim (partial meniscectomy) is usually quicker than after a repair, which needs time to heal and often comes with weeks of limits on bending or weight-bearing. Your surgeon will give you a timeline, and their protocol comes first.
This article is general information, not a substitute for an individual assessment.
Sources
- Kise NJ, et al. Exercise therapy versus arthroscopic partial meniscectomy for degenerative meniscal tear in middle aged patients: randomised controlled trial with two year follow-up. BMJ 2016;354:i3740. https://doi.org/10.1136/bmj.i3740
- van de Graaf VA, et al. Effect of early surgery vs physical therapy on knee function among patients with nonobstructive meniscal tears: the ESCAPE randomized clinical trial. JAMA 2018;320(13):1328–1337. https://doi.org/10.1001/jama.2018.13308
- Culvenor AG, et al. Prevalence of knee osteoarthritis features on magnetic resonance imaging in asymptomatic uninjured adults: a systematic review and meta-analysis. Br J Sports Med 2019;53(20):1268–1278. https://doi.org/10.1136/bjsports-2018-099257
Related: Meniscus tear · Knee pain physio in Manchester · Knee pain when bending · ACL reconstruction · Post-operative rehab · All conditions we treat
Reviewed by Nick Chatziviltsos, PgDip, HCPC-registered physiotherapist (PH114351).