

Ankylosing spondylitis (AS), part of a condition now called axial spondyloarthritis, is an inflammatory arthritis of the spine. Its biggest clue is surprising: unlike most back pain, it gets better with movement and worse with rest, often waking people in the second half of the night. On average, people wait almost 7 years for a diagnosis. Treatment is led by a rheumatologist, and NICE recommends a structured exercise programme with a specialist physio alongside medication.
Key takeaways
- Clues to inflammatory back pain: started before 45, lasted over 3 months, stiffness that eases with movement, waking in the second half of the night, buttock pain.
- Diagnostic delay averages 6.7 years worldwide, and it isn't getting shorter.
- It affects women as well as men, and can be present even if a blood test (HLA-B27) or X-ray is normal.
- NICE (2017) recommends a structured exercise programme including stretching, strengthening, breathing, spinal mobility and aerobic exercise.
- Exercise slightly improves function and may reduce pain, but it works alongside medical treatment, not instead of it.
What is ankylosing spondylitis?
Axial spondyloarthritis is a long-term inflammatory condition that mainly affects the joints of the spine and the sacroiliac joints, where the spine meets the pelvis. "Ankylosing spondylitis" is the older name, now usually used for the form where changes show on X-ray. Some people have the same condition without X-ray changes (non-radiographic axial spondyloarthritis).
Over time, inflammation can cause stiffness and, in some people, parts of the spine can fuse. Modern medicines, combined with regular exercise, aim to control inflammation and keep you moving.
Is my back pain inflammatory?
Most back pain is "mechanical": it's worse with activity and better with rest. Inflammatory back pain tends to behave the other way round.
| Mechanical back pain (most common) | Inflammatory back pain (possible axial SpA) |
|---|---|
| Any age, often after a strain | Usually starts before age 45 |
| Better with rest | Better with movement, worse with rest |
| Short-lived morning stiffness | Long morning stiffness |
| Rarely wakes you because of stiffness | Waking in the second half of the night |
| Settles within weeks | Lasts more than 3 months |
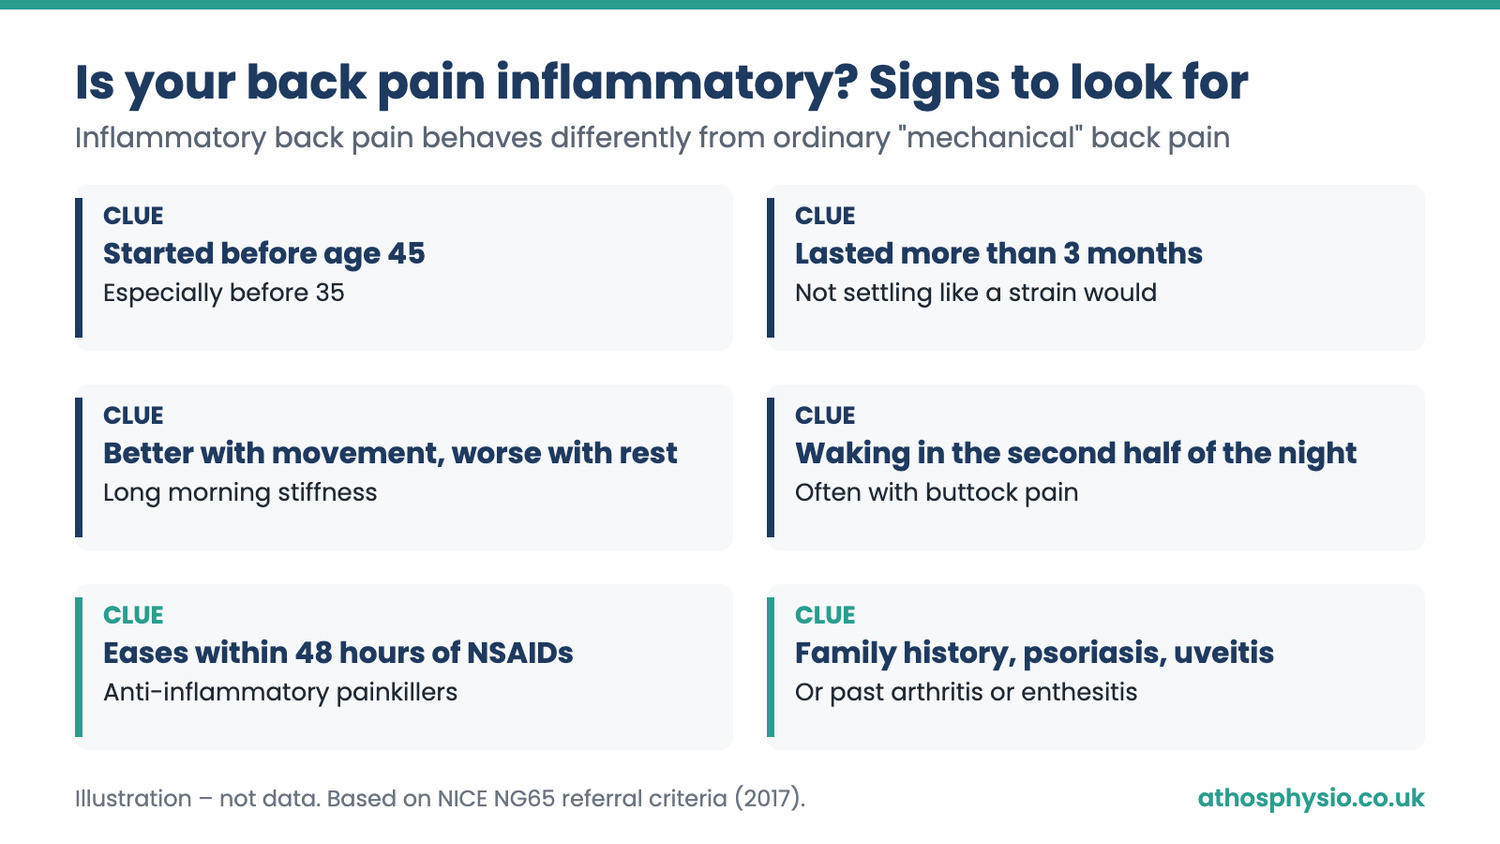
NICE's referral guide (NG65): if back pain started before 45 and has lasted more than 3 months, NICE advises referral to a rheumatologist if 4 or more of these are present:
- back pain that started before age 35
- waking in the second half of the night because of symptoms
- buttock pain
- improvement with movement
- improvement within 48 hours of taking anti-inflammatories (NSAIDs)
- a parent, sibling or child with spondyloarthritis
- current or past arthritis, enthesitis (pain where tendons attach to bone, such as the heel) or psoriasis
With exactly 3, NICE advises an HLA-B27 blood test, and referral if it's positive.
The myth: "It's a young man's disease, and a normal X-ray rules it out"
AS was long thought of as a condition of young men. NICE now says axial spondyloarthritis affects a similar number of women as men, can occur in people who are HLA-B27 negative, and may be present despite a normal X-ray of the sacroiliac joints.
That helps explain the delay. A 2021 meta-analysis found the average time from symptoms to diagnosis was 6.7 years, with no improvement over time. Longer delays were linked with younger age at onset and with not having symptoms outside the joints, such as eye inflammation (uveitis), psoriasis or inflammatory bowel disease.

What this means: if your back pain matches the inflammatory pattern, ask your GP about a rheumatology referral, even if you've been told it's "just back pain".
What does exercise do for ankylosing spondylitis?
NICE recommends referring people with axial spondyloarthritis to a specialist physiotherapist for an individualised, structured exercise programme including:
- stretching, strengthening and posture exercises
- deep breathing
- spinal extension and range of motion exercises for the lower, middle and upper back
- aerobic exercise
It also suggests considering hydrotherapy as an add-on.
A 2019 Cochrane review of 14 trials (1,579 people) found moderate- to low-quality evidence that exercise programmes probably slightly improve function, may reduce pain, and probably slightly reduce disease activity compared with no exercise. Compared with usual care, the extra benefit was small or absent. Most people in the trials were also taking medication.
Reading this critically: the effects are modest, and many trials had a high or unclear risk of bias. But exercise is low-risk, helps general health, and keeps you mobile, which is why international recommendations (ASAS-EULAR 2022) still put non-drug treatment, including exercise, alongside anti-inflammatories as first-line care.
A daily movement routine
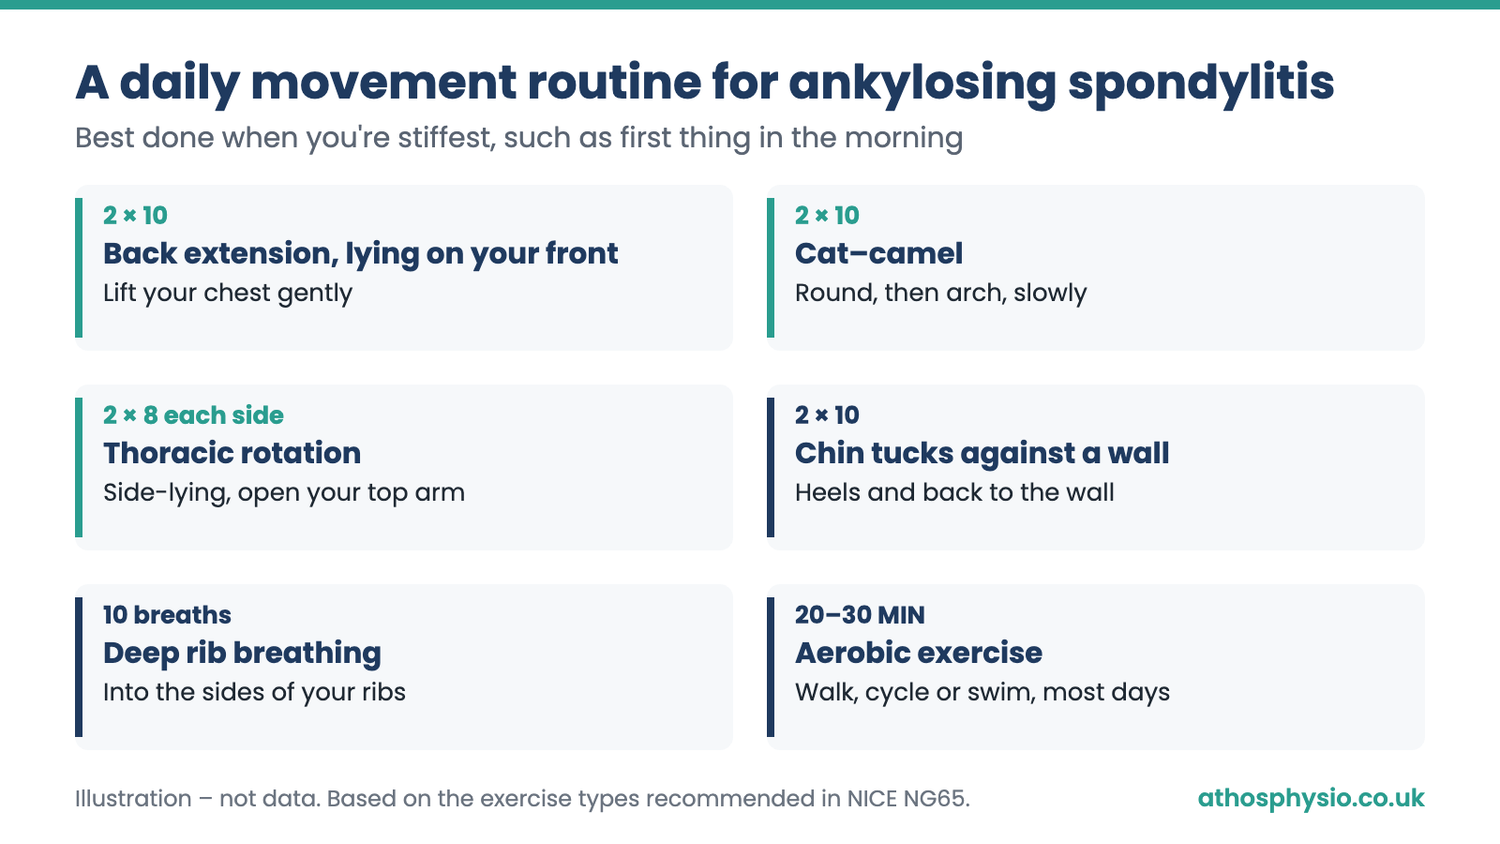
Do these most days, ideally when you're stiffest, such as first thing in the morning. Move within a comfortable range, and stop any exercise that causes sharp pain.
| Exercise | How | Dose |
|---|---|---|
| Back extension (lying on your front) | Lift your chest gently, keeping your hips down | 2 × 10 |
| Cat–camel (on hands and knees) | Round, then arch your back slowly | 2 × 10 |
| Thoracic rotation (side-lying) | Open your top arm to the ceiling, following it with your eyes | 2 × 8 each side |
| Chin tucks against a wall | Stand with heels and back to the wall, gently tuck your chin | 2 × 10 |
| Deep breathing | Breathe into the sides of your ribs, hold 3 seconds | 10 breaths |
| Aerobic exercise | Brisk walking, cycling or swimming | 20–30 minutes, most days |
Add strengthening for your back, hips and legs 2–3 times a week. A specialist physio can tailor the programme to how your spine moves and adjust it as things change.
When to get urgent help
Contact your GP or rheumatology team urgently if you have:
- a red, painful eye with blurred vision or sensitivity to light (possible uveitis: same-day assessment is needed)
- a sudden severe increase in back pain after a minor fall or injury, as a stiff spine can fracture more easily
- a high temperature with a flare-up
Call 999 or go to A&E if you have new numbness around your genitals or bottom, or problems with bladder or bowel control.
How we help at Athos Physio
Our clinic is inside F45 Manchester NQ, at 77 Piccadilly in Manchester city centre. If your back pain sounds inflammatory, we'll explain why and point you to your GP for a rheumatology referral. If you already have a diagnosis, we can build a custom rehab and strengthening plan to work alongside your medical treatment, focused on mobility, strength, breathing and fitness. You don't need a GP referral, and we work with Bupa, WPA, Vitality and Aviva. Book an appointment, or read about back and neck pain physio.
FAQs
What are the first signs of ankylosing spondylitis?
Typically, low back or buttock pain that started before 45, has lasted more than 3 months, is stiff in the morning, improves with movement and wakes you in the second half of the night. Some people also have heel pain, eye inflammation or psoriasis.
Is exercise good for ankylosing spondylitis?
Yes. NICE recommends a structured programme of stretching, strengthening, breathing, spinal mobility and aerobic exercise. Research shows it probably slightly improves function and may reduce pain, alongside medical treatment.
Can women get ankylosing spondylitis?
Yes. NICE notes that axial spondyloarthritis affects a similar number of women as men, though women have historically been diagnosed later.
Can physiotherapy cure ankylosing spondylitis?
No. It's a long-term condition managed by a rheumatology team, often with medication. Physiotherapy and exercise help you stay mobile, strong and active, and manage pain and stiffness.
This article is general information, not a substitute for an individual assessment.
Sources
- NICE. Spondyloarthritis in over 16s: diagnosis and management (NG65), 2017. https://www.nice.org.uk/guidance/ng65
- Regnaux JP, et al. Exercise programmes for ankylosing spondylitis. Cochrane Database Syst Rev 2019;10:CD011321. https://doi.org/10.1002/14651858.CD011321.pub2
- Zhao SS, et al. Diagnostic delay in axial spondyloarthritis: a systematic review and meta-analysis. Rheumatology (Oxford) 2021;60(4):1620–1628. https://doi.org/10.1093/rheumatology/keaa807
- Ramiro S, et al. ASAS-EULAR recommendations for the management of axial spondyloarthritis: 2022 update. Ann Rheum Dis 2023;82(1):19–34. https://doi.org/10.1136/ard-2022-223296
Related: Back and neck pain physio · Lower back pain · Upper back pain · Chronic pain · All conditions we treat
Reviewed by Nick Chatziviltsos, PgDip, HCPC-registered physiotherapist (PH114351).